



In a medical IT system, the first insulation fault should not shut down the operating room. That continuity—designed to keep a clinical procedure from being placed at the mercy of a single electrical anomaly—carries a less visible obligation: the fault must be located and corrected before another one appears.
The insulation monitor raises the alarm, but it does not complete the diagnosis. It shows that insulation resistance has fallen below the established threshold; the hospital still needs to know which outgoing circuit is affected, which device or cable section is responsible and when maintenance can intervene without transferring risk to the patient. Insulation fault location in medical IT systems turns that uncertainty into a circuit address and, with it, an actionable decision.
Electrical continuity does not mean pretending the fault is not there. It means giving the hospital a clean, supervised margin of time: enough to find the wound without stopping the room’s pulse.
The first fault does not shut down the operating room, but it starts a countdown
In a conventional earthed network, a fault may produce enough current to operate a protective device. In a medical IT power supply system, the source is isolated from earth or connected to it through a high impedance. When the first insulation fault occurs, current is limited by the circuit impedance and the network’s distributed capacitance, allowing the supply to remain available in the intended applications.
This behaviour protects clinical continuity, but it does not restore the insulation. The installation remains in a degraded state. If a second fault appears on another live conductor, the architecture that allowed the area to continue operating may face a far more severe condition. The first alarm is therefore not an invitation to wait; it is a call to locate the fault precisely.
The 2021 edition of IEC 60364-7-710 for medical locations expressly includes insulation fault location systems in its requirements. The technical reason reflects the operational reality of a hospital: maintaining the supply only makes sense when there is also a reliable way to find and eliminate the degradation.
| State | What happens | Technical priority |
|---|---|---|
| Normal operation | Insulation resistance remains above the configured threshold | Continuous supervision and periodic testing |
| First fault | An alarm is generated, but the area can remain energised | Identify the outgoing circuit and prepare a controlled intervention |
| Persistent fault | The network operates in a degraded condition for longer | Prevent the alarm from becoming normalised and shorten the time to repair |
| Second fault | A high current may flow between points affected by different faults | Operation of protective devices and possible loss of continuity |
Detection and location are not the same thing
An insulation monitoring device observes the IT network as a whole. Its role is to measure resistance to earth continuously and issue an alarm when the value crosses the defined limit. IT insulation monitoring therefore answers the first question: is there a degradation that requires attention?
The general alarm does not necessarily reveal whether the source is an operating table, a power supply, a flexible cable, a socket outlet, a luminaire, a fixed wiring section or an accumulation of small leakage currents. If several outgoing circuits share the same panel, searching through successive disconnections can be slow and, during clinical activity, simply unacceptable.
A location system adds selectivity to the diagnosis. It correlates a test signal with the measuring current transformers assigned to each outgoing circuit and determines through which channel the fault-related current returns. The message changes from “there is a fault on this network” to “the fault is on this circuit”.

| Function | Information provided | Decision enabled |
|---|---|---|
| Insulation monitoring | Insulation value and the presence of an alarm condition | Recognise that the IT network has entered a degraded state |
| Test-signal injection | A limited, recognisable locating signal | Make the electrical path of the fault traceable |
| Channel-based location | The outgoing circuit or group of circuits carrying the signal | Narrow down the circuit before intervention |
| On-site verification | The specific device, socket or wiring section responsible | Repair, verify and restore normal conditions |
How the system identifies the affected outgoing circuit
The principle is straightforward. When the monitor detects insufficient insulation resistance, the test-current generator superimposes a limited signal on the network. The signal travels through the live conductors, crosses the fault point, returns through the protective conductor and closes the measuring circuit.
The live conductors of each outgoing circuit pass through their corresponding measuring current transformer. The locator scans the channels and identifies the one carrying the signature of the locating signal. Because each transformer, channel and circuit has already been mapped, the technical team receives a useful electrical address rather than an undifferentiated alarm.
IEC 61557-8 defines the requirements for devices that continuously monitor insulation resistance in IT systems. IEC 61557-9 covers equipment designed to locate insulation faults. The functions are related, but distinct: one recognises the overall condition; the other follows its path through the distribution system.
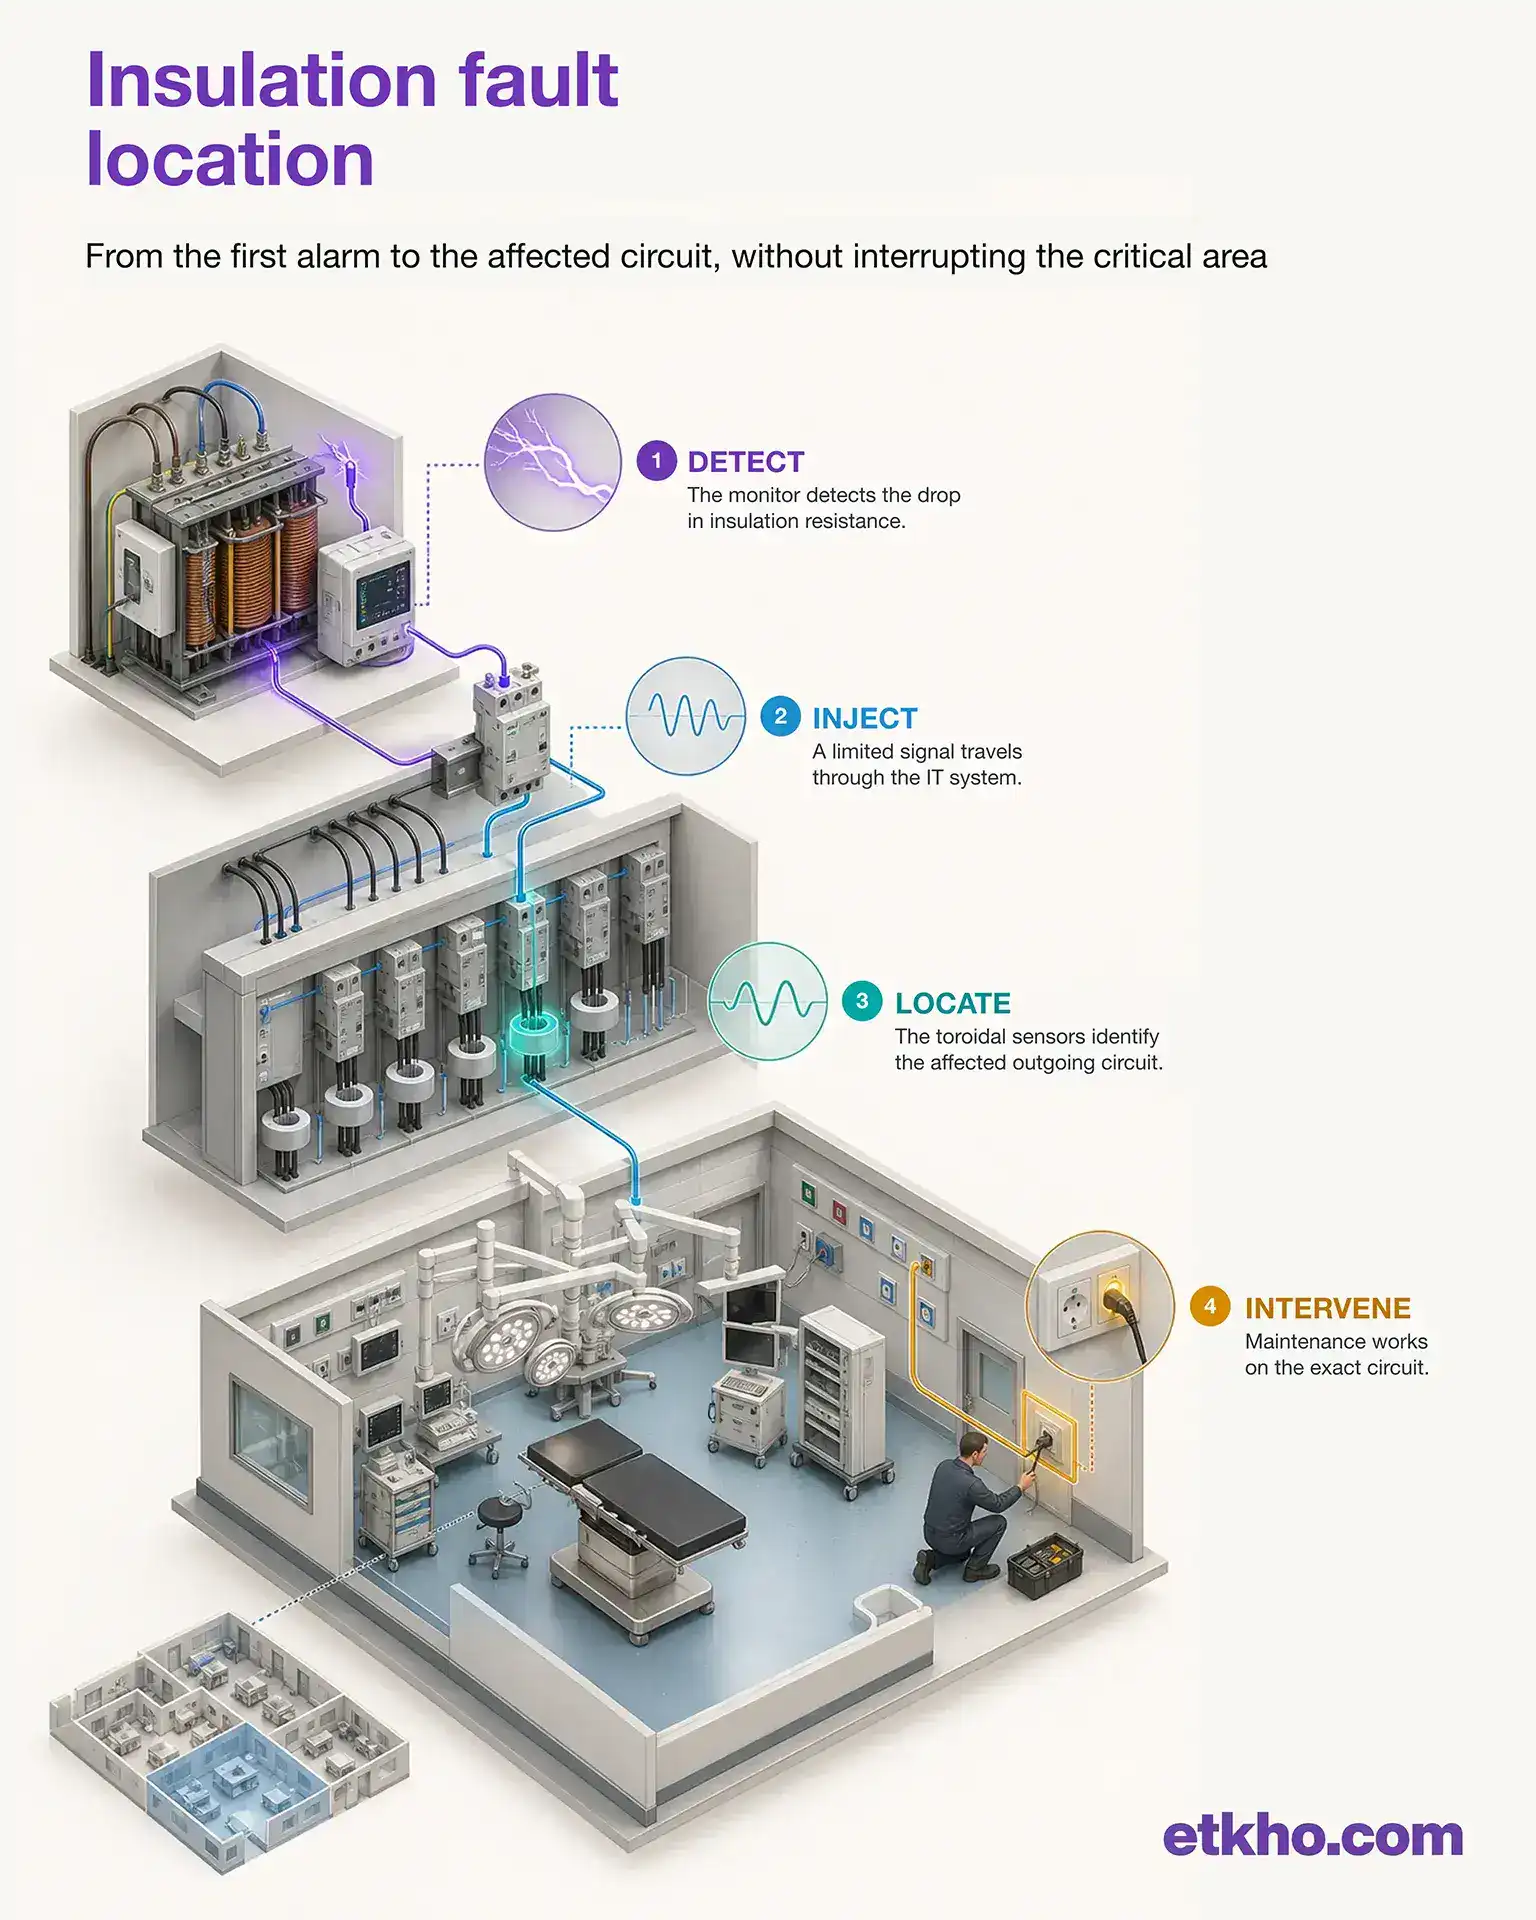
Three devices, one diagnostic chain
Reliable location depends on monitoring, signal injection and evaluation operating as a single system. An isolated device can generate data; the complete chain produces an address and communicates it in a form that maintenance can act upon.
ES 1000A: recognising degradation and preserving its context
The ETKHO ES 1000A insulation monitor supervises AC installations with connected DC components and, in addition to insulation resistance, monitors load current and medical isolation-transformer temperature. Its real-time clock associates stored alarms with a date and time—an important detail when an event must be correlated with room activity or the connection of a particular device.
The ES 1000A technical data sheet specifies an adjustable insulation threshold and RS485 communication with repeaters, multi-repeaters and fault-location equipment. The important point is not merely that an alarm appears, but that it reaches the correct location, retains its timestamp and can be distinguished from overload, overtemperature or communication faults.

ES 449: introducing a signal the system can follow
The ES 449 current injector operates with the ES 1000A and the ES 448 locator network. It generates the locating signal that reaches the measuring current transformers connected to the locator modules. It does not reproduce a real fault or increase its severity; it creates a limited reference that the system can distinguish and trace.
The ES 449 technical documentation specifies RS485 communication with the insulation monitor and the locator network. That coordination prevents the search from becoming an improvised manoeuvre: it is part of the supervision architecture.
ES 448: turning six possible paths into one identified channel
The ES 448 scans six measuring channels connected to toroidal transformers. When it identifies the signal on an outgoing circuit, it illuminates the corresponding channel indicator and transmits the alarm address to the ES 1000A via RS485. According to its technical data sheet, up to seven locator modules can be combined with one monitor, and an automatic test is performed every hour.
The number of channels is only useful when it reflects the actual installation. Each measuring current transformer must enclose the live conductors of its assigned circuit; the protective conductor must not pass through it. The drawing reference, physical label, device address and name displayed by the supervision system must all describe the same outgoing circuit. When those four layers diverge, the technology may indicate the correct channel while the hospital interprets it incorrectly.

From alarm to circuit: a protocol with no room for shortcuts
An effective response begins long before an electrical panel is opened. The hospital must already have decided who receives the alarm, what information they need, how they coordinate with clinical staff and under what conditions an outgoing circuit may be isolated. Without that prior agreement, even an exact location can lead to a late or unnecessarily disruptive intervention.
- Confirm the nature of the alarm. Distinguish an insulation fault from load, temperature, earth-connection or communication alarms.
- Place the event in context. Record the time, area, panel, measured value and clinical activity. An intermittent alarm may coincide with a device being connected or moved.
- Read the located channel. Verify the module address and the correspondence between channel, outgoing circuit, drawing and physical labelling.
- Assess immediate criticality. Establish which loads the circuit supplies and agree with the clinical lead when the next test can be performed.
- Narrow down the faulty element. Within the identified circuit, inspect connected equipment, socket outlets, flexible leads, fixed wiring and environmental conditions using authorised procedures.
- Intervene selectively. Disconnect only when the clinical situation and safety procedure allow it, avoiding turning a targeted search into a general outage.
- Repair and verify. Confirm the recovery of insulation resistance, check that alarms have reset and document the cause, action and result.
The response should be integrated with the hospital’s technical alarm management. Clinical staff need a clear signal rather than a flood of electrical detail; maintenance, by contrast, must retain the value, address, time and event sequence. The same incident requires two levels of interpretation.
Where the fault often hides
The first fault does not always begin inside the panel. It often appears in the final metre, where the fixed installation meets daily use: repeatedly flexed cables, plugs exposed to strain, mobile equipment, socket outlets near intensive cleaning or components affected by moisture and ageing.
The source may also be a section of containment, a connection, an electromagnetic compatibility filter or electronic equipment connected to the network. In extensive installations, distributed leakage capacitance can influence the measurement and must be considered when thresholds and architecture are defined. Not every drop in resistance has the same cause, and not every intermittent alarm is false.
| Observed pattern | Reasonable hypothesis | Useful check |
|---|---|---|
| Alarm when a particular device is connected | Fault or leakage associated with the device or its cable | Correlate timestamp, socket outlet and connected device |
| Alarm when a table or trolley is moved | Flexible cable, plug or mechanically stressed point | Controlled inspection of the moving path and its connections |
| Progressive decline over several days | Moisture, ageing or cumulative degradation | Compare trends, environmental conditions and circuits |
| Several channels appear to be affected | Assignment error, coupling or common fault | Review conductor routing through transformers, drawings and configuration |
| Alarm without a located channel | Fault outside monitored circuits or insufficient locating signal | Check coverage, wiring, communication and design |
Why location can fail even when every device is working
Result accuracy does not depend on electronics alone. A conductor routed through the wrong measuring current transformer, an extension that never reached the drawings or a duplicated bus address can destroy traceability without causing an obvious equipment failure. The system remains powered, but the meaning of the channel has become uncertain.
The most expensive errors are often silent: outgoing circuits grouped with insufficient granularity, critical loads left outside the location scheme, labels describing an earlier distribution layout or tests that merely confirmed the equipment powered up. When a real alarm arrives, maintenance discovers that it knows the panel but not the path.
The solution is to test the installation’s complete chain of meaning. During hospital commissioning, controlled faults should be simulated on representative outgoing circuits, verifying that the physical channel, monitor message, repeater, supervision system and drawing all identify the same location. The check should be repeated after refurbishments or load changes.
What should be recorded after every alarm
An alarm resolved without a record leaves the hospital exposed to repeating the same investigation. At a minimum, the technical report should retain the date and time, insulation value, located channel, connected equipment, clinical activity, confirmed cause, corrective action and the value measured after repair.
This history separates isolated incidents from patterns. If the same outgoing circuit accumulates alarms, if the value falls under particular environmental conditions or if one type of device appears repeatedly, maintenance stops chasing episodes and begins to recognise behaviour. Predictive maintenance in hospitals and critical areas begins with precisely this kind of well-preserved technical memory.
Designing the installation so the fault can be located
Fault location should not be added as a late accessory. It is designed when the number of outgoing circuits per panel, the required granularity, measuring-transformer positions, channel identification and the information sent to the supervision system are decided.
An operating room with many mobile loads may require a different strategy from an ICU with repeated bed spaces or a technical room with fixed equipment. The greater the impact of interrupting an outgoing circuit to find the fault, the more valuable it is for the location system to provide a precise address before the installation is touched.
ETKHO integrates monitoring, signalling and location through the ES 1000A, the ES 449 current injector and ES 448 locator modules, together with repeaters and communication with supervision systems. Selection and configuration should begin with the single-line diagram, circuit count, load criticality and the hospital’s operating protocol. ETKHO’s hospital electrical safety advisory service helps organise those variables before they are translated into equipment.
Frequently asked questions about insulation faults in medical IT systems
Should the operating room be disconnected after the first insulation fault?
Not automatically merely because it is the first fault. A medical IT system is designed to maintain continuity in its intended applications, generate an alarm and allow a controlled intervention. The precise response must follow the hospital’s procedure and an assessment of the affected load.
What is the difference between an insulation monitor and a fault locator?
The monitor measures the overall condition of the network relative to earth and generates the alarm. The locator scans the channels assigned to the outgoing circuits and identifies the one carrying the locating signal, narrowing the fault down to a circuit.
Does the locator identify the faulty device directly?
It identifies the affected outgoing circuit or channel. Within that circuit, maintenance must establish whether the source is a device, cable, socket outlet or fixed installation using authorised test procedures.
Can the network continue operating while the alarm is active?
It can maintain the supply after a first fault, but it is operating in a degraded condition. Extending that condition increases exposure to a second fault, so the alarm must be located, assessed and corrected as a priority.
When should the fault-location system be tested?
During commissioning, as part of periodic verification and after refurbishments, extensions, panel alterations or changes to the supervision system. The test must confirm the complete path from the simulated fault to the message received.
What information does maintenance need to respond quickly?
Area, panel, insulation value, date and time, module address, channel, associated circuit, connected loads and the room’s clinical status. Agreement between the display, drawing and physical label is essential.
Make sure every alarm arrives with an address
If you need to define fault-location coverage, review the correspondence between channels and circuits or integrate insulation monitoring into a new critical area, contact ETKHO’s technical advisory team.
Technical sources
- IEC 60364-7-710:2021 — Requirements for electrical installations in medical locations.
- IEC 61557-8:2014 — Insulation monitoring devices for IT systems.
- IEC 61557-9:2014 — Equipment for insulation fault location in IT systems.
- ETKHO — ES 1000A insulation monitor technical data sheet.
- ETKHO — ES 448 leakage locator technical data sheet.
- ETKHO — ES 449 current injector technical data sheet.